

Transparent Lifeline Against Malnutrition (T-LAMP)
T-LAMP (Transparent Lifeline Against Malnutrition Project) is a five-year, evidence-based nutrition programme designed and led by Civil Society – Scaling Up Nutrition in Nigeria (CS-SUNN).
- Period
- March-August 2026
- Where
- Kwali Primary Health Care Centre
About T-LAMP
T-LAMP (Transparent Lifeline Against Malnutrition Project) is a five-year, evidence-based nutrition programme designed and led by Civil Society – Scaling Up Nutrition in Nigeria (CS-SUNN). It targets severe acute malnutrition (SAM), moderate acute malnutrition (MAM) and maternal anaemia, and it works with the Nutrition Society of Nigeria, the FCT Primary Health Care Board and the National Primary Health Care Development Agency (NPHCDA). The project responds to a serious gap in Nigeria’s nutrition system.
Treatment reaches only about 20% of SAM cases. Funding is short, and stockouts and diversion of RUTF (ready-to-use therapeutic food) are common. Many families drop out of treatment because of transport costs and financial strain. Even among treated children, 31% relapse within six months. T-LAMP was built to close three gaps: funding, accountability for commodities, and relapse. It rests on two pillars. The first is digital transparency and accountability. A web platform and dashboard track each child’s enrolment, weekly measurements and commodity use, and support photo documentation.
The aim is to prevent diversion and double-treatment. The longer-term design also uses crowdsourced and institutional funding to fill RUTF and micronutrient supply gaps, with real-time tracking so donors can see where resources go. The second pillar is a Relapse Prevention Package, which continues support after treatment. It includes post-discharge follow-up, caregiver counselling, food demonstrations, home gardening, WASH education and, in some cases, cash transfers linked to clinic attendance and growth monitoring.
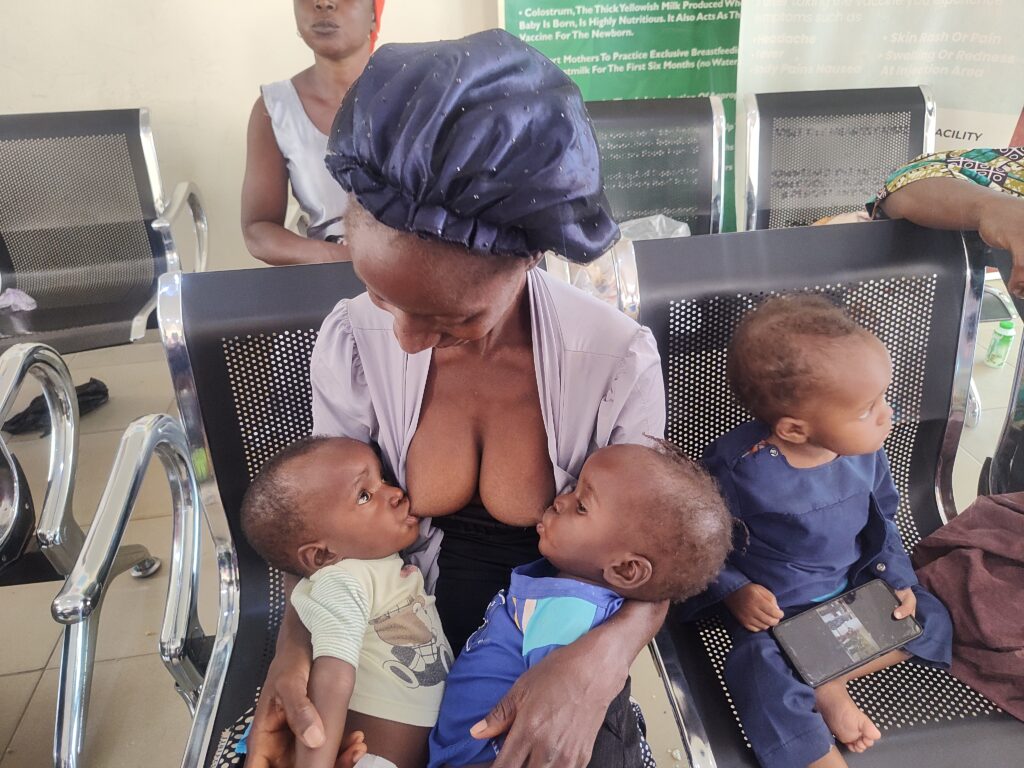
The first test was a proof of concept at Kwali Primary Health Care Centre in the Federal Capital Territory, from March to August 2026. Twenty children aged 6 to 59 months were treated with weekly RUTF and routine medical care for up to 12 weeks, and recovered children then moved into a three-month follow-up programme with Tom Brown complementary food and growth checks. Fourteen children (70%) fully recovered and two (10%) improved from SAM to MAM, giving 80% overall improvement.
No child died, the default rate was 10%, and two children were referred for specialist care. Existing health workers ran the digital monitoring after light-touch orientation. The pilot showed that digital accountability and post-discharge support can be added to Nigeria’s existing IMAM (Integrated Management of Acute Malnutrition) system without disrupting routine services. It was small, so the team presents it as evidence of feasibility, not a final measure of effectiveness.
Next steps include longer post-discharge follow-up, a cost-benefit and scalability analysis, and a stakeholder validation workshop with the Nutrition Society of Nigeria, NPHCDA and Kwali PHC staff. The team then plans a larger multi-site study, pilots in Kaduna and Kano, and moving the dashboard into government nutrition information systems. The longer-term aim is national scale-up backed by domestic funding and philanthropy, with eventual handover to government ownership.
Why it matters
Nigeria has the second-highest number of stunted children in the world. Projections for 2024–25 put 5.4 million children at risk of acute malnutrition, including about 1.8 million with severe acute malnutrition (SAM), the deadliest form. Only about 20% of SAM cases nationally receive treatment. The 2025 UNICEF appeal had a 68% funding gap, which led to RUTF stockouts and a black market. Even treated children relapse: 31% within six months. In Kwali, 642 children have been registered since 2018 at the IMAM site, and many defaulted because of transport costs, stockouts and financial strain. Last year, 32 SAM and 64 MAM cases were identified during Maternal, Newborn and Child Health Week, and the clinic could not treat them because it was out of RUTF.
What Changed
T-LAMP on the ground
Our approach
- Found children early Outreach and routine clinic screening checked children aged 6–59 months using MUAC and tests for swelling (oedema).
- Treated children at the clinic Each child got a weekly RUTF ration plus routine medical care, including antibiotics, deworming and malaria treatment.
- Tracked every child digitally The T-LAMP dashboard logged enrolment, weekly measurements, commodity use and photos, so no child or sachet went unaccounted for.
- Visited homes when things went wrong Health workers made home visits for every missed appointment and for any child whose condition worsened.
- Taught caregivers Counselling covered infant and young child feeding, dietary diversity, hygiene, handwashing and recognising danger signs.
- Kept supporting children after discharge Recovered children joined a three-month follow-up programme with Tom Brown and growth checks.
- Assessed each household’s risk A questionnaire on food access, dietary variety and feeding practices guided how much extra support each family needed.
- Worked through partners CS-SUNN led delivery, the FCT Primary Health Care Board provided the service backbone, and the Nutrition Society of Nigeria supplied technical expertise.
Lessons for scale-up
Talk to the programme team
Partner with CS-SUNN to fund the next phase, bring the dashboard into government nutrition systems